Medicine Needs More Than a Doctor’s Authority
A doctor’s training and experience are essential to medical care, but they do not automatically settle every question about what should be done. A treatment may be medically possible while still raising difficult questions about a patient’s wishes, the risks involved or who should receive limited resources.
That is why medical ethics asks not only what a clinician believes is best, but also how a decision can be justified to the people it affects. Patients, families and the wider public may bring perspectives that differ from a doctor’s. A responsible decision must make room for those voices rather than treating professional authority as the only measure of what is right.
Medical ethics offers a shared language for people who may disagree about the answer but still need to reason through the decision together.
Kim Jun-hyuk, a medical ethicist and professor at Yonsei University, describes the field as one that brings medicine into conversation with philosophy, law, sociology and even engineering. In technical terms, it is interdisciplinary—a field that draws on different areas of knowledge rather than relying on just one.
Why Bringing Disciplines Together Is Difficult
Calling a subject interdisciplinary does not necessarily mean that all the fields involved have equal influence. In many collaborations, one discipline sets the main questions and standards, while others are added around it. For example, a university program might combine technology and social science, yet still give greater weight to the technical field when deciding what counts as useful knowledge.
Some approaches to interdisciplinary study seek to connect many kinds of knowledge within one overarching explanation. The idea of “consilience,” for instance, has been used to describe efforts to link knowledge across fields. But bringing different disciplines together under one explanatory framework is not the same as allowing them to retain distinct perspectives and challenge one another.
Medical ethics has a particular reason to resist letting one voice dominate. Medicine is central to the field, and medical expertise matters. Yet medical knowledge alone cannot determine every question about the right course of action: it can help explain what a treatment may do, but it cannot by itself decide how much risk a patient should accept or how care should be distributed fairly.
From Professional Duty to Shared Justification
Ideas about a doctor’s duties have a long history. The Hippocratic tradition is often associated with the responsibility to care for patients and avoid causing harm. That tradition remains important, but modern medical ethics asks a broader question: is a medical action justified simply because a doctor believes it is appropriate?
The answer matters because people receiving care are not merely subjects of medical decisions. They have their own values, priorities and understanding of what a worthwhile outcome means. A treatment that extends life, for example, may not be the choice a patient wants if its burdens conflict with the patient’s goals.
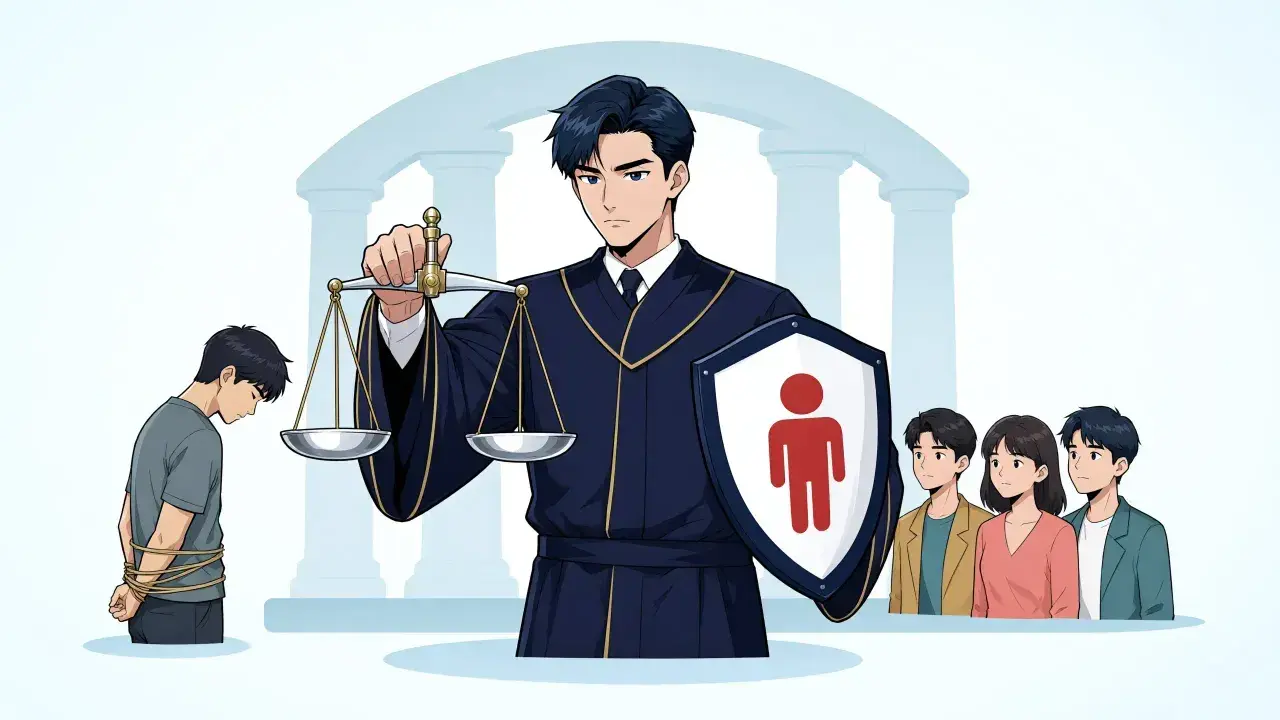
Modern medical ethics therefore seeks reasons that can be examined beyond the medical profession itself. Patients and citizens, as well as people working in law and philosophy, need to be able to question those reasons. The goal is not to make every person agree, but to make decisions explainable and open to challenge.
Four Principles for Examining Difficult Decisions
A major influence on this approach is The Principles of Biomedical Ethics, first published in 1979 by Tom Beauchamp and James Childress. Alongside the Belmont Report, published that same year and influential in research ethics, the book helped establish a framework for discussing and evaluating decisions in medicine and biomedical research.
The book is associated with four principles. They are not a checklist that automatically produces the right answer; rather, they offer different questions to consider when a decision affects people’s health, choices or access to care.
- Respect for autonomy (respecting a person’s ability to make informed choices): Patients and research participants should be given understandable information and have their decisions taken seriously. In practice, this means explaining the likely benefits and risks of a treatment rather than asking someone to agree without understanding what is involved.
- Beneficence (acting to promote another person’s well-being): Care should aim to help people and prevent or reduce harm. A clinician might consider whether a treatment is likely to improve a patient’s health or quality of life.
- Nonmaleficence (avoiding harm): Medical decisions should take seriously the possibility of injury, suffering or other negative effects. A treatment’s potential benefit must be considered alongside its risks, not treated as a reason to ignore them.
- Justice (fairness in how benefits and burdens are shared): Decisions should avoid unjust discrimination and consider how care, resources and risks are distributed. This principle becomes especially important when a health system must decide how to allocate something limited, such as specialist appointments or emergency treatment.
A Framework, Not a Formula
These principles can point in different directions. A patient may refuse a treatment that a doctor believes could help. A medical intervention may offer a possible benefit but carry serious risks. A health service may have to weigh one person’s needs against the fair use of resources for others.
The framework does not make such conflicts disappear. Instead, it helps people identify what is at stake and explain why they give greater weight to one concern in a particular case. The principles are broad, so they must be interpreted in context: what counts as a meaningful choice, a likely benefit or a fair allocation can depend on the circumstances.
Agreeing on ethical principles does not mean reaching the same conclusion. It means being willing to explain a decision using reasons that others can examine.
How the Principles Work in Real Life
Consider a patient deciding whether to undergo a major operation. The doctor may focus on the chance that surgery will extend the patient’s life, while the patient may be more concerned about pain, recovery time or the ability to live independently. Respect for autonomy asks whether the patient understands the options and whether their preferences are heard; beneficence and nonmaleficence draw attention to possible benefits and harms.
Justice can enter the discussion in less obvious ways. If a treatment is scarce or costly, questions may arise about who can access it and whether similar patients are being treated consistently. The point is not that every bedside decision should become a lengthy debate about the health system. Rather, the principle reminds decision-makers that fairness can matter alongside the needs of the person in front of them.
These examples show why no single principle can settle every case. A doctor cannot simply invoke “the patient’s best interests” without considering what the patient values. Nor can a patient’s choice be discussed responsibly without clear information about the likely consequences. Ethical judgment means examining how the principles apply together, including where they conflict.
The Limits of Principle-Based Ethics
The approach has critics. Some argue that broad principles can be too abstract to resolve the details of a real dispute. Others question whether the principles rest on a sufficiently complete theory of morality. In other words, a short list of shared standards may tell people what to discuss without telling them exactly how to decide.
That limitation is real, but it does not make the framework useless. People do not always need to share one comprehensive theory of right and wrong before they can reason together. They may begin from different beliefs yet still recognize that patients should be informed, avoidable harm matters and resources should not be distributed unfairly.
The principles are most useful when they guide inquiry rather than replace it. Treating them like an answer key risks making a complex decision look simpler than it is. Using them as a basis for discussion requires each person to explain what a principle means in the case at hand and how they are balancing it against the others.
Keeping Different Voices in the Conversation
The broader lesson is that ethical medical care involves more than technical skill. Clinicians bring knowledge about diagnoses and treatments; patients bring first-hand knowledge of their lives and priorities. Families, researchers, legal experts and society may also have legitimate concerns, depending on the decision.
A shared framework cannot guarantee agreement, and it should not be expected to. Its value lies in making disagreement more constructive: people can ask what is being protected, whose interests are affected and whether the reasons offered can be defended to those who bear the consequences.
For Kim Jun-hyuk, this is what makes medical ethics genuinely interdisciplinary. It does not try to erase the differences among medicine, law, philosophy and the lived experience of patients. Instead, it creates a common language in which those perspectives can meet, challenge one another and contribute to a reasoned decision.
The central question is not simply who has the authority to decide. It is whether the decision can be explained, examined and justified without silencing the people it affects.